
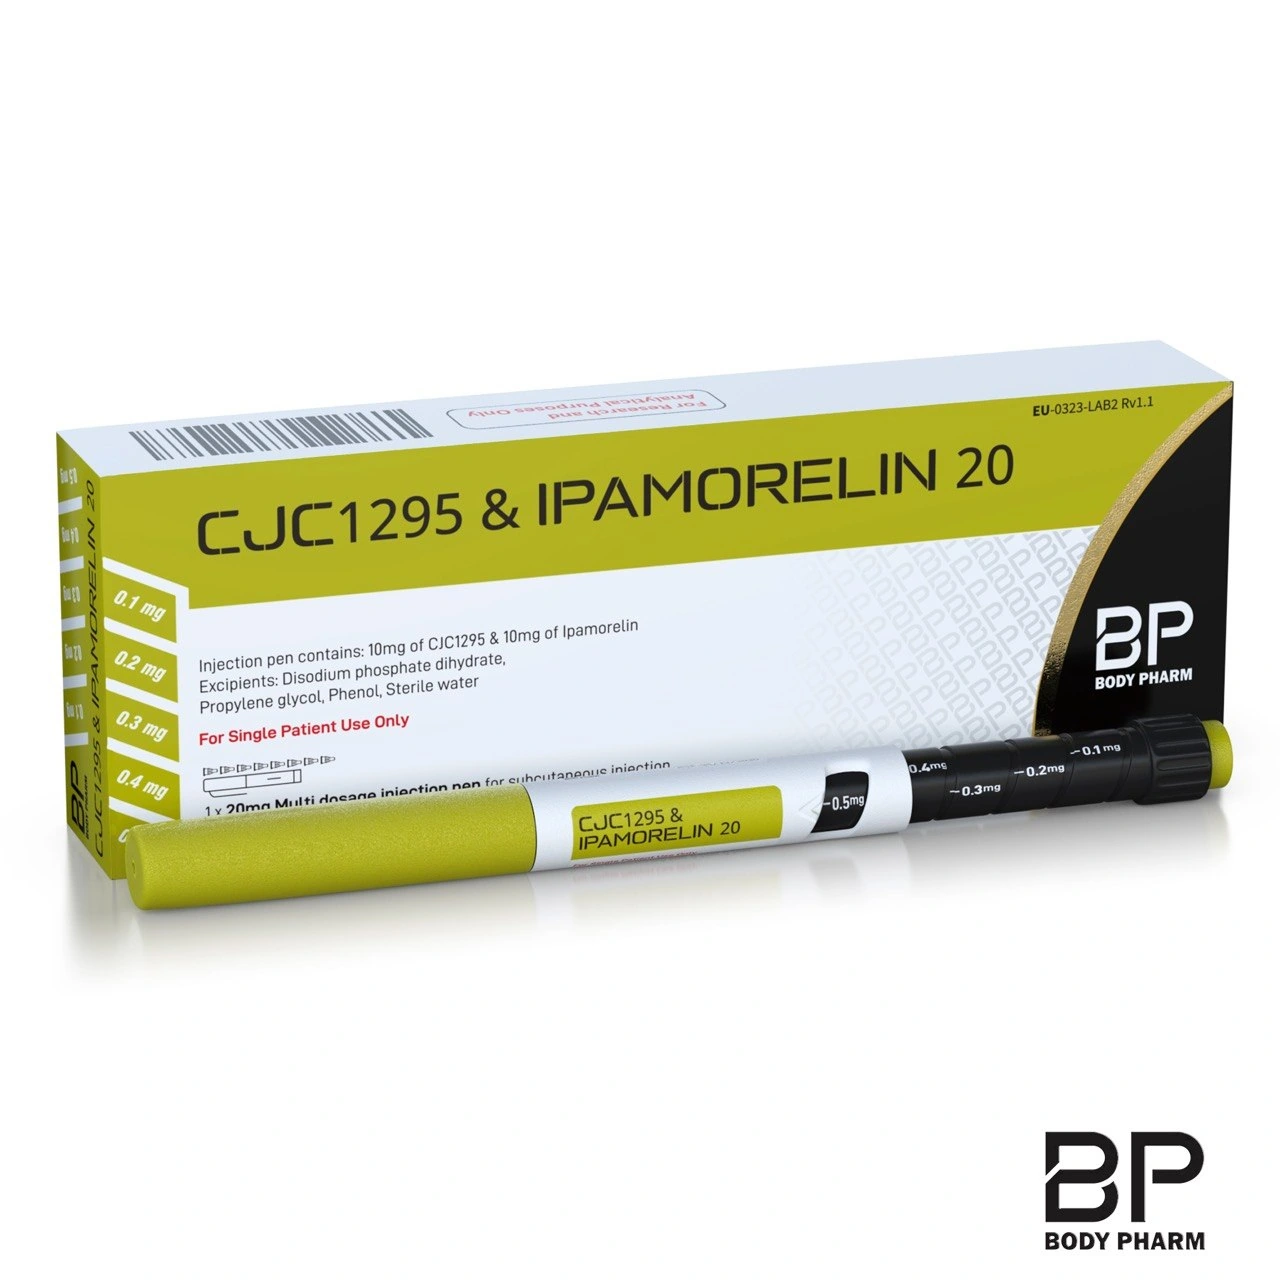
CJC/Ipamorelin is not another name for Somatropin. Somatropin supplies recombinant growth hormone, while CJC/Ipamorelin is discussed in relation to hormone-release signaling. The distinction remains even when both products are presented in similar pens.
For a Bali resident or visitor, the key decision is not which device looks more convenient. It is whether the clinical question concerns replacing a diagnosed deficiency or evaluating a different proposed intervention.
Why the similar appearance can mislead
A pen is a delivery format. It does not identify the biological role of its contents. Products that look alike can contain different molecules, use different units and have different evidence.
The CJC/Ipamorelin listing describes a blend. The Somatropin listing describes another ingredient. Reading both as “HGH pens” removes information needed for a meaningful comparison.
| Starting point | Question to resolve |
|---|---|
| A diagnosed GH deficiency | What treatment is prescribed for that diagnosis? |
| A general energy or recovery concern | What is causing the concern? |
| Interest in CJC/Ipamorelin research | Was the exact proposed intervention studied? |
| A change during travel | Who is responsible for the clinical transition and follow-up? |
What replacement means
Somatropin is recombinant human growth hormone. Its medicinal uses include defined replacement settings; the GENOTROPIN label describes a particular pharmaceutical product, not every pen carrying a Somatropin name. Read the prescribing information.
Replacing a hormone and stimulating pathways involved in its release are different interventions. One cannot be assumed to replace the other simply because both appear in discussions of GH or IGF-I.
For someone already receiving prescribed treatment, a switch is therefore a clinical decision. Product availability alone does not answer it.
What hormone-release research establishes
A study of long-acting CJC-1295 in healthy adults measured GH and IGF-I secretion. It did not test whether the catalogue's CJC/Ipamorelin blend replaces Somatropin in a patient with deficiency. Read the original CJC study.
The phrase “raises a hormone” is narrower than “produces the same treatment result.” An accurate comparison preserves that gap instead of filling it with assumptions.
The exact CJC identity also matters. The existing CJC blend and DAC guide covers that naming question separately, so it does not need to be mistaken for proof of a clinical substitution.
How a diagnosis changes the comparison
The Endocrine Society's adult GH-deficiency guideline emphasizes appropriate diagnostic evaluation and usually stimulation testing, with defined exceptions. Treatment decisions depend on the person's clinical situation. Read the guideline.
A person with an established pituitary diagnosis is not in the same position as someone who wants better gym recovery. A comparison that ignores this difference may present a valid treatment in one setting as an answer to an unrelated goal.
This is why an isolated low-energy complaint or a laboratory number should not be used to select a pen independently of clinical assessment.
Keep continuity clear during a Bali stay
If you are continuing an existing plan while living in Umalas or staying in Canggu, keep the prescription, exact product and responsible clinician identifiable. When discussing another product, show its actual details.
Ask the clinician which part of the proposed intervention would be equivalent, if any, and which part would change. That invites a specific answer rather than an impression based on two product names.
If you will return overseas, establish who reviews the plan after departure. Records should remain understandable to the next clinician, not depend on a chat message that says only “switched to peptides.”
Judge the comparison by its answer
A useful explanation should connect the proposed intervention to the original clinical question. It should identify what would be measured and what would count as an unwanted change. It should not rely only on “natural,” “strong” or “anti-aging.”
Those adjectives do not establish replacement equivalence, and they do not explain why a person would benefit from changing an existing plan.
Frequently asked questions
Does “stimulates your own GH” make CJC/Ipamorelin automatically preferable?
No. That describes a proposed pathway, not an individual comparison of outcomes or safety.
Can I convert a Somatropin amount into CJC/Ipamorelin?
The shared topic does not provide a dose conversion. This article supplies no substitution protocol.
Does a change in IGF-I prove equivalent treatment?
A biomarker alone cannot establish every clinical outcome or equivalence between preparations.
What should I bring to a consultation?
The reason for the comparison, existing diagnosis and prescription if any, relevant reports and the exact proposed product.
Sources and further reading
- GENOTROPIN prescribing information — Pfizer. Source checked 2026-10-19.
- CJC-1295: GH and IGF-I secretion in healthy adults — Teichman et al., JCEM. Source checked 2026-10-19.
- Adult Growth Hormone Deficiency guideline — Endocrine Society. Source checked 2026-10-19.